

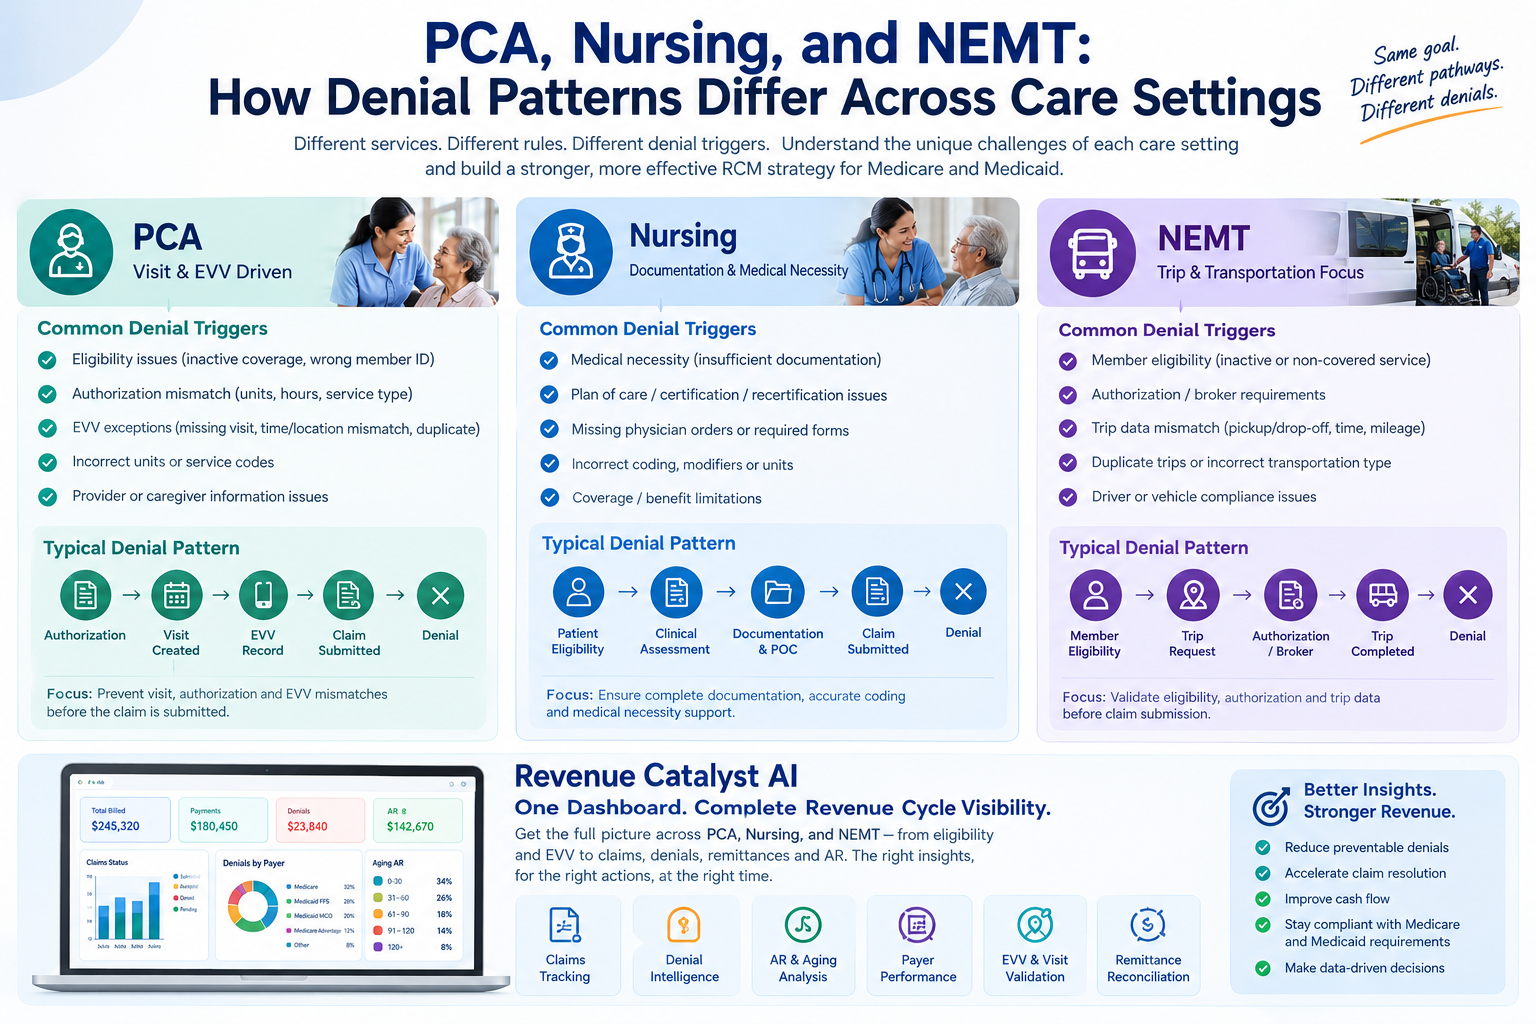
Denials are not created equal. The reasons a PCA claim is denied can be very different from the reasons a skilled nursing or NEMT claim fails. Understanding these differences is essential for building a stronger Medicare and Medicaid revenue cycle.
For healthcare providers, a denial is often treated as a simple billing problem:
Claim submitted → Claim denied → Biller fixes it → Claim resubmitted.
But that approach misses an important reality.
Different care settings create different revenue-cycle risks.
A Personal Care Assistant (PCA) service may depend heavily on eligibility, authorization, EVV, service units, and visit data.
A skilled nursing or home health claim may be more dependent on medical necessity, documentation, certification, plan of care, coding, and Medicare coverage requirements.
An NEMT claim may depend on member eligibility, trip authorization, transportation type, pickup/drop-off information, broker requirements, trip records, and state-specific Medicaid rules.
So while all three may end with a claim denial, the underlying causes can be completely different.
For organizations managing multiple care services, understanding these differences is critical.
Why Denial Patterns Differ by Care Setting
A claim is essentially the financial representation of a service that was delivered.
But the information required to prove that service was:
- Authorized
- Eligible
- Correctly delivered
- Properly documented
- Correctly coded
- Billable
- Compliant with payer requirements
depends on the type of service.
Consider these three examples:
PCA
“Was the authorized caregiver at the right place, at the right time, providing the authorized service?”
Nursing
“Was the skilled service medically necessary, properly ordered, documented, and supported by the patient’s plan of care?”
NEMT
“Was the eligible member transported for an authorized covered purpose, using the appropriate transportation service, with the required trip information?”
These are fundamentally different billing questions.
That is why a one-size-fits-all denial strategy is rarely enough.
1. PCA Denials: The Visit and Authorization Problem
Personal Care Assistant services are particularly sensitive to visit-level data.
For Medicaid-funded personal care services subject to EVV, federal requirements are designed to capture information such as the service provided, beneficiary, caregiver, date, start and end time, and location.
That means the billing process depends heavily on whether the actual service record matches what the payer expects.
Common PCA denial triggers
Eligibility problems
The member may:
- Not be eligible on the date of service
- Have inactive coverage
- Have a mismatched member ID
- Be assigned to a different payer or managed-care plan
Authorization mismatch
The service may exceed the authorized:
- Units
- Hours
- Service type
- Service period
For example:
Authorization: 20 hours
Billed: 24 hours
The additional units may create a billing problem.
EVV mismatch
Examples include:
- Missing visit
- Incorrect start time
- Incorrect end time
- Location mismatch
- Caregiver mismatch
- Service mismatch
- Duplicate visit
- EVV record not matching claim data
Incorrect units
The claim may contain a different number of units from the underlying visit record.
Provider or caregiver issues
Depending on the program and payer, problems can also arise from provider enrollment, caregiver information, or required program credentials.
The PCA Denial Pattern
PCA denials often follow this pattern:
Authorization
↓
Scheduled Visit
↓
Caregiver Visit
↓
EVV Record
↓
Billing Data
↓
Claim
↓
Payer Validation
If something breaks anywhere in that chain, the claim can become problematic.
That makes PCA denial prevention heavily dependent on data consistency.
The question for the billing team should be:
Does the claim accurately represent the authorized and verified visit?
2. Nursing Denials: Documentation and Medical Necessity
Nursing claims have a different risk profile.
For Medicare home health, CMS states that coverage requires, among other things, that the patient be homebound, under the care of a physician or allowed practitioner, receive services under an established and periodically reviewed plan of care, and meet the applicable skilled-service requirements.
This creates a very different denial environment from PCA.
The question is not simply:
“Did the caregiver complete the visit?”
The payer may need to determine:
“Was this service medically necessary and adequately supported by the required documentation?”
Common Nursing Denial Triggers
Medical Necessity
The documentation may not sufficiently demonstrate why the skilled service was required.
CMS reported that for the 2024 Medicare home health reporting period, insufficient documentation accounted for 51.4% of improper payments, followed by medical necessity at 33.7%. Incorrect coding accounted for 3.4%, while no documentation accounted for 2.3%.
This illustrates why documentation should be treated as a revenue-cycle issue, not simply a clinical issue.
Plan of Care Problems
Claims can be affected when required information related to the plan of care is incomplete, inconsistent, or not appropriately supported.
The billing team therefore needs visibility into:
- Plan-of-care status
- Certification
- Recertification
- Orders
- Required documentation
- Dates of service
- Supporting clinical information
Coding Errors
A claim may contain:
- Incorrect procedure code
- Incorrect diagnosis
- Incorrect modifier
- Incorrect units
- Incorrect claim information
Even when the service was legitimately provided, incorrect coding can prevent appropriate payment.
Documentation Gaps
Documentation is particularly important because it provides the evidence connecting:
Patient Condition → Medical Need → Ordered Service → Delivered Service → Billed Service
If one of those links is weak, the claim can become vulnerable.
The Nursing Denial Pattern
A typical nursing denial risk looks more like:
Patient Eligibility
↓
Clinical Assessment
↓
Medical Necessity
↓
Order / Certification
↓
Plan of Care
↓
Service Documentation
↓
Coding
↓
Claim
↓
Medical Review / Adjudication
That is why nursing denial prevention requires stronger clinical-documentation and billing-data validation.
CMS also maintains standardized review reason codes and statements for Medicare claim and prior-authorization reviews, reflecting the importance of understanding the specific reason behind a review-related denial rather than treating all denials as the same.
3. NEMT Denials: The Trip and Transportation Problem
NEMT creates another completely different denial environment.
Medicaid’s transportation benefit is intended to assure transportation for eligible beneficiaries to covered services, and CMS has specifically examined NEMT delivery models, program integrity, provider requirements, documentation, and correct billing.
For NEMT, the core billing record is not primarily a clinical visit.
It is a trip.
The billing question becomes:
Was the correct eligible member transported for an appropriate covered purpose, using the authorized transportation service, and is the trip record complete and billable?
Common NEMT Denial Triggers
Member eligibility
The member may not have active Medicaid coverage for the date of service.
Trip authorization
The transportation may require an authorization or broker-approved trip.
Trip mismatch
The claim may not match the underlying trip record.
Examples:
- Wrong pickup location
- Wrong drop-off location
- Incorrect date
- Incorrect mileage
- Incorrect transportation level
- Incorrect trip type
Duplicate trips
The same trip may accidentally be submitted more than once.
Broker mismatch
Where broker-managed arrangements are involved, the provider may need to reconcile trip information received through the broker with the transportation provider’s own records.
Driver or vehicle requirements
Depending on state and program requirements, transportation providers may also need to satisfy applicable provider and driver requirements.
CMS’s Medicaid NEMT materials specifically identify provider enrollment, eligibility determinations, correct billing, documentation, and data requirements as program-integrity topics.
The NEMT Denial Pattern
The NEMT revenue cycle often looks like:
Member Eligibility
↓
Trip Request
↓
Authorization / Broker
↓
Trip Scheduled
↓
Trip Completed
↓
Trip Data
↓
Claim
↓
Payer / Broker Validation
↓
Payment
The important difference is that the trip record becomes the foundation of the claim.
If the trip data is incomplete or inconsistent, the billing problem can start before the claim is ever created.
PCA vs Nursing vs NEMT: The Key Difference
Here is the simplest way to understand the three environments:
| Care Setting | Primary Billing Evidence | Common Risk Areas |
| PCA | Visit + EVV + Authorization | EVV, units, authorization, eligibility |
| Nursing | Clinical documentation + POC + Claim | Medical necessity, documentation, coding |
| NEMT | Trip + Authorization + Transportation Data | Eligibility, trip data, authorization, broker requirements |
This is why one generic denial workflow is not enough.
Each setting requires a different validation strategy.
The Same Denial Rate Can Mean Completely Different Things
Imagine three providers each report:
5% denial rate
At first glance, they appear to have identical performance.
But look deeper.
PCA
Most denials are:
EVV + authorization
This indicates a visit-data validation problem.
Nursing
Most denials are:
Documentation + medical necessity
This indicates a clinical documentation and compliance problem.
NEMT
Most denials are:
Trip mismatch + authorization
This indicates a trip-data and transportation workflow problem.
The percentage is identical.
The solution is completely different.
That is why an RCM dashboard should show denial reasons and root causes, not just denial rates.
Why Medicare and Medicaid Require Different Thinking
Medicare and Medicaid are not interchangeable billing environments.
For Medicare home health, CMS describes a structured benefit with specific eligibility and coverage requirements, including homebound status, plan of care, certification, and skilled-service requirements.
Medicaid is more complex from an operational perspective because states administer their Medicaid programs within federal requirements, and specific service, EVV, managed-care, and billing workflows can vary.
This is particularly important for:
- PCA
- Personal care
- Home and community-based services
- Medicaid home health
- NEMT
The same service category may therefore have different operational requirements across state programs and payers.
A strong RCM platform must be able to account for these differences rather than treating every claim identically.
The Problem With Reactive Denial Management
A traditional billing process often looks like this:
Claim Submitted
↓
Claim Denied
↓
Biller Opens Claim
↓
Biller Finds Problem
↓
Claim Corrected
↓
Claim Resubmitted
↓
Wait for Payment
This is reactive.
The problem is that the agency has already spent time and potentially delayed revenue.
A better approach is:
Service Data
↓
Validation
↓
Rule Checking
↓
Potential Issue Identified
↓
Correction
↓
Clean Claim
↓
Submission
↓
Payment
This is denial prevention.
What Revenue Catalyst AI Can Do Across These Care Settings
This is where a multi-service RCM platform becomes particularly valuable.
Revenue Catalyst AI can support different care settings by applying the appropriate validation logic to the type of service being billed.
Instead of asking:
“Is this claim correct?”
the system can ask:
“Is this claim correct for this service, this payer, and this billing scenario?”
For PCA: Validate the Visit Before the Claim
Revenue Catalyst AI can help connect:
Authorization → Visit Data → EVV → Billing Data → Claim
Potential issues can be identified around:
- Eligibility
- Authorization
- Service type
- Units
- Visit information
- EVV-related discrepancies
- Duplicate billing
- Payer-specific requirements
The objective is to prevent a visit-data problem from becoming a denied claim.
For Nursing: Validate the Documentation and Billing Context
For nursing and applicable Medicare/Medicaid home health workflows, Revenue Catalyst AI can help support validation around:
- Eligibility
- Authorization
- Service information
- Coding
- Required claim data
- Documentation-related billing checkpoints
- Payer-specific rules
For Medicare home health in particular, this is important because CMS identifies documentation and medical necessity as major sources of improper payments.
The goal is not to replace clinical judgment.
It is to help ensure that billing data is consistent with the information required for successful claim processing.
For NEMT: Validate the Trip Before Billing
For NEMT, the workflow can focus on:
Member → Authorization → Trip → Transportation Data → Claim
Revenue Catalyst AI can help identify potential issues such as:
- Eligibility
- Authorization
- Trip information
- Service type
- Units
- Duplicate trips
- Payer/broker requirements
- Billing inconsistencies
This allows transportation providers to identify potential billing problems before they become aged AR.
One RCM Platform, Different Denial Intelligence
The real advantage is not treating PCA, Nursing, and NEMT as identical.
It is doing the opposite.
Revenue Catalyst AI can apply service-specific validation logic while maintaining a common revenue-cycle framework.
PCA
Prevent Visit & EVV Denials
Nursing
Prevent Documentation, Medical Necessity & Coding Risks
NEMT
Prevent Trip, Authorization & Eligibility Denials
And across all three:
Validate → Submit → Monitor → Analyze → Recover → Prevent
Denial Management Should Become Root-Cause Management
A mature RCM process should not stop at:
“The claim was denied.”
It should ask:
What happened?
Claim denied.
Why?
Authorization exceeded.
Where?
Medicaid PCA.
How much?
$4,250.
Is it recurring?
Yes—same payer and service category.
Can it be prevented?
Potentially—validate authorized units before claim generation.
That final question is the most important one.
Because the objective of denial management is not simply to recover yesterday’s revenue.
It is to prevent tomorrow’s denials.
A Better Denial Dashboard for Multiple Care Settings
For organizations supporting PCA, Nursing, and NEMT, the dashboard should allow management to filter denial performance by:
- Care setting
- Payer
- State
- Service
- Provider
- Location
- Denial reason
- Claim type
- Dollar value
- Aging
- Resolution status
For example:
PCA
EVV Denials: 42
Authorization Denials: 31
Nursing
Documentation Denials: 18
Medical Necessity Denials: 11
NEMT
Trip Data Denials: 27
Authorization Denials: 14
This gives leadership a much clearer picture than a single organization-wide denial percentage.
From Denial Patterns to Preventive Rules
The ultimate goal should be a feedback loop.
Step 1 — Identify
A recurring denial appears.
Step 2 — Analyze
The system identifies the common characteristics.
Step 3 — Validate
The same conditions are checked before future claims are submitted.
Step 4 — Prevent
Potentially problematic claims are flagged or corrected.
Step 5 — Measure
The organization tracks whether the denial pattern decreases.
This creates a continuous improvement cycle:
Denial → Root Cause → Rule → Prevention → Measurement
That is where AI-enabled RCM can provide significantly more value than a basic claims reporting system.
What This Means for Home Care and Transportation Providers
The biggest lesson is simple:
There is no single “denial problem.” There are different denial patterns created by different care-delivery models.
PCA depends heavily on:
Authorization + EVV + Visit Data
Nursing depends heavily on:
Medical Necessity + Documentation + Coding
NEMT depends heavily on:
Eligibility + Authorization + Trip Data
And all three ultimately depend on:
Accurate data + payer rules + clean claims + effective follow-up.
A strong RCM strategy therefore needs to understand the care setting before it evaluates the claim.
